Psychiatry - O. K. Napreyenko 2001
Clinical Psychiatry
Psychosomatic and Somatopsychic Disorders
In the Charmides, Plato wrote: "...the greatest error in the Treatment of sickness is that there are physicians for the body and physicians for the soul, since the two cannot be separated... For where the whole is unwell, a part of it cannot be well".
More than 2,000 years later, the Hippocratic school of Kos contrasted the dynamic-humoral-spiritual (essentially psychosomatic) concept with the mechanistic-organic approach of the Cnidian school.
Renowned philosophers Descartes, Spinoza, and Leibniz affirmed the promise of the views held by Plato, Kos, and their followers. Descartes developed The Theory of psychophysical dualism, formulating a doctrine on the interrelation between the body and consciousness. Spinoza argued in his anthropological theory that whatever happens to the body has a counterpart in the soul, and the soul itself is nothing other than the "idea of the body." Leibniz considered the harmony of bodily and mental processes to be the foundation of psychophysical interaction.
These and many other historical scientific orientations laid the groundwork for modern Perspectives on Psychosomatic and Somatopsychic Disorders.
Psychosomatic disorders (a term coined by Heinrot in 1918) are defined as secondary functional and organic disorders of Internal Organs and systems whose primary cause of onset and exacerbation lies in psychological factors.
Somatopsychic disorders (a term introduced by Jacobi in 1822) are psychiatric disorders that develop secondarily in the course of somatic illnesses unrelated to the Brain. The latter include pathological conditions of the cardiovascular, respiratory, digestive, urogenital, and endocrine systems, The Musculoskeletal System, eyes, Blood, and Skin, as well as extracranial oncological diseases, and pathologies of Pregnancy and the postpartum period, among others.
According to WHO experts, nearly 50% of inpatient hospital beds worldwide are occupied by patients with psychosomatic pathology.
As evidenced by our research findings (O. K. Napreenko, 1991), nearly 70% of somatic patients exhibit mental disorders of various ranges and degrees of severity.
However, prevalence rates of psychosomatic and somatopsychic disorders vary due to differing views on their clinical boundaries, The Diversity of epidemiological settings in various regions, and inconsistent interpretations of these conditions by different specialists.
Etiology AND Pathogenesis
To understand the Causes and Mechanisms underlying these disorders, it is useful to review the characteristics of normal psychosomatic relationships. Only by mastering them can one discern the fragile boundary between health and pathology.
Under normal conditions, the mutual Influence of the psyche and soma is most vividly manifested during emotional reactions—such as joy, anger, or fear. When a person is deeply agitated, we say: "my Heart skipped a beat," "I had a lump in my throat," "I turned pale or flushed," "a weight was lifted from my chest," and so forth. All these figurative expressions point to somatic changes that occur during emotional experiences. Psychosomatic deviations can also stem from the emotional component. A striking illustration of this reaction was demonstrated by mischievous children who walked in front of a brass band holding lemons in their hands, causing the musicians to stop playing due to excessive salivation.
The latter example demonstrates the possibility of psychosomatic reactions occurring via the first signaling system. However, the starting point can also be an action mediated through the second signaling system.
For instance, when a lemon is described verbally, its image is secondarily evoked in the imagination, and consequently, a corresponding reaction is triggered in the somatic sphere.
Physiological reactions to mental processes can occur in various bodily organs and systems: The Cardiovascular system (changes in heart rate and blood pressure, vasoconstriction or vasodilation causing pallor or flushing); the Respiratory system (acceleration, deceleration, or breath-holding); the Digestive System (increased or decreased motility of The Stomach and intestines, nausea, vomiting, increased or diminished salivation); the Reproductive System (erection, lubrication, etc.); and the muscular system (tremor, stupor, excitability), among others. An example of combined somatopsychic processes is the sensation of hunger that arises when the stomach is empty. This brings about dissatisfaction, tension, and heightened mental and physical activity aimed at achieving satiety. The physiological baseline of this sensation is hypoglycemia, which develops when nutrient intake is insufficient. This in some way affects brain Cells. Similar psychological changes occur during bodily fluid depletion when a person experiences thirst.
Psychosomatic relationships can also acquire a persistent pathological character. For example, a feeling of fear triggers palpitations, which in turn leads to the thought of heart damage. Such suspicion increases fear and intensifies discomfort in the cardiac region. Here we are dealing with what is known as positive feedback.
The Nature of these relationships largely depends on the individual's constitutional traits. Thus, in response to emotional stress, reactions may manifest in the cardiovascular system, the digestive organs, the Muscles, and so on.
Numerous Examples can be cited illustrating unusual manifestations of pathological psychosomatic influences.
For instance, Cannon observed a Voodoo tribe in Central Africa that had lived in isolation for generations. Over time, its members grew so dependent on one another that the most severe punishment was banishment from the tribe. For these unfortunates, this was an absolute psychological catastrophe—after a few days of solitude, they would die without any physical violence.
The most probable cause of death is cardiac arrest resulting from arrhythmia and coronary spasm. This type of sudden death was named after the tribe—"voodoo death."
An interesting case occurred with the French writer Flaubert. While describing the poisoning of his novel's heroine with arsenic, he imagined it so vividly that certain symptoms of poisoning manifested in himself.
Models of similar relationships have also been created in experiments. For example, at the Sukhumi monkey colony, researchers observed persistent vascular changes in male monkeys after Separation from a female with whom they had long shared a cage. The female was placed in the cage of another male, who would court her right in front of her former "mate." As a result of prolonged "indignation," the jealous male developed nervous exhaustion, followed by a persistent rise in blood pressure.
Valuable data have been obtained through the observation of patients with gastric fistulas by studying Changes in the gastric mucosa. In states of frustration, emotional depression, mental discomfort, resentment, or anger, gastric activity increases, the mucosa reddens, and its secretory function changes. If these emotional states persist for a long time, tissue membrane fragility increases. Furthermore, repeated psychotraumatic situations lead to mucosal erosions, punctate hemorrhages, and frequently, peptic ulcers.
The etiology and pathogenesis of psychosomatic disorders remain not fully elucidated. Their genesis is likely multifactorial. Various aspects are explained by the Specificity theory, which points to specific (unconscious) conflicts that cause specific disorders (F. Alexander). There are also certain personality profiles prone to particular groups of psychosomatic illnesses (F. Dunbar). According to the non-specific theory, any stress can trigger pathological changes in a genetically vulnerable "Shock organ" (locus minoris resistentiae). According to H. Selye's theory, excessive cortisol secretion resulting from the hypothalamic-pituitary-adrenal axis response to stress leads to structural changes in organs and systems. G. Engel notes that in response to stressful situations, some individuals develop a "give-up-thiazide/defeat complex" (depressive mood, helplessness, and hopelessness) that disrupts homeostatic balance, increasing susceptibility to infectious and other pathogenic factors. Significant contributions have also been made by the theories of cortico-visceral interactions (expanding upon the ideas of neurism and conditioned Reflexes by I. P. Pavlov) and P. Anokhin's functional systems theory, among others.
The most comprehensive classification of psychosomatic disorders was first proposed by M. Bleuler (1970), who divided them into three main types.
I. The so-called classical psychosomatoses, i.e., psychosomatic diseases accompanied by organic pathology of internal organs and systems. These include essential or idiopathic Hypertension (unrelated to infection or physical irritation), and PEPTIC ULCER DISEASE. This category also encompasses coronary artery disease, Bronchial Asthma triggered by stressful situations, inflammatory bowel diseases (Crohn's disease, Ulcerative Colitis), neurodermatitis, idiopathic urticaria, and certain endocrine pathologies, among others. This is a rather small group.
II. Functional psychosomatic disorders, which are the most commonly observed. They tend to have a protracted and persistent course. In some cases, they are classified as systemic neuroses. These include functional cardiac reactions (certain types of arrhythmias, angina pectoris, coronary spasms), syncope (fainting), hypotension, headaches, Raynaud's disease, stuttering, enuresis, neurotic tics, vomiting, irritable bowel syndrome, most forms of sexual dysfunction, and functional Infertility, among others.
III. Psychosomatic disorders in a broader (indirect) sense. Health is impaired due to specific human behavioral patterns driven by personality traits and emotional experiences. Notable examples include a predisposition to physical trauma, Burns, psychogenic obesity, alcoholism, and substance abuse.
Based on a review of over 70 studies, Burene concluded that individuals prone to occupational or domestic injuries are typically undisciplined, irresponsible, inaccurate, and careless.
In many individuals, hyperphagia (overeating) serves to alleviate feelings of anxiety. The quality and quantity of food can also act as an indicator of one's psychosocial standing. For instance, N. Mailer argued: "Politicians cannot afford to be thin. Thin people in high positions do not inspire trust. In nations that have long suffered from famine, food often plays The Role of a reward, and its Abundance is a sign of prosperity and prestige. The desire to put on weight can serve as a defense against an unwanted marriage or a compensation for social defeat." A telling example is provided by R. Konečný and M. Bouhal (1983), who quote an excessively overweight woman: "You wonder why I love to eat so much? But do I have anything else in this world besides food?".
The causes underlying The Development of psychological dependence on toxic substances (alcohol, certain medications, tobacco, etc.) are primarily linked to a person's character traits, emotional experiences, and micro- and macro-social environments. Physical dependence develops during the Second Stage of the illness, and its consequences may include A wide variety of organic somatic disorders.
Smoking is associated with mild local changes in the Upper Respiratory Tract and a higher incidence of pulmonary and cardiovascular diseases. Alcoholism and substance dependence can lead to toxic myocarditis and myocardial dystrophy, hepatitis and Liver cirrhosis, pancreatitis, polyneuritis, encephalopathy, and many other alterations that frequently result in death.
B. Luban-Plozza et al. (1977) distinguish the following groups of psychosomatic disorders: 1) psychosomatoses; 2) functional syndromes (similar to Bleuler's classification); 3) conversion symptoms.
The latter arise in response to a neurotic conflict, carry a symbolic meaning, and manifest primarily as pathological phenomena affecting sensory Functions (amaurosis, mutism, pain, anesthesia) or disrupting motor activity (paralysis, paresis, convulsions, astasia, abasia, vomiting, aphonia, hysteric globus), among others.
METABOLISM/2.html">THE CONCEPT OF "psychosomatics" encompasses a range of phenomena that are difficult to define ambiguously. However, two main aspects can be distinguished: psychosomatic disorders and psychosomatic medicine.
Psychosomatic medicine defines a general approach to medical care based on the conceptual framework of somato-psychosocial interaction during the development, course, and treatment of illnesses.
In the DSM-IV, psychosomatic disorders are designated under Category 316 — "Psychological Factors Affecting Medical Condition." This also includes disorders with general somatic symptoms caused by or contributing to emotional factors. Typically, this refers to The system of individual organs whose activity is regulated by the Autonomic Nervous system, such as atopic dermatitis, low back pain, bronchial asthma, hypertension, migraine, peptic ulcer disease, and colitis.
They are classified as follows: 316 ... (specify the psychological factor influencing the condition, followed by the name of the somatic or neurological disease).
Disease names should be selected based on the Factors influencing the course of the somatic or neurological condition, namely:
1) mental disorder;
2) psychological symptoms;
3) patient personality traits or psychological defense mechanisms;
4) maladaptive health-related behaviors;
5) physiological response to stress;
6) other or unspecified psychological factors.
In the ICD-10, the term "psychosomatic" is avoided to prevent the misconception that psychological factors do not play a role in the development of other diseases. Disorders described as psychosomatic in other classifications can be categorized as follows.
F45 — somatoform disorders; F50 — eating disorders; F52 — sexual dysfunctions; F54 — psychological and behavioral factors associated with disorders or diseases
classified elsewhere. Category F54 is particularly important. It is used to denote the emotional origin of physical disorders classified in other (non-psychiatric) chapters of the ICD-10. Examples include: asthma (F54 plus J45); dermatitis and eczema (F54 plus L23 — L25); urticaria (F54 plus L40); peptic ulcer disease (F54 plus K25); mucous colitis (F54 plus K58); ulcerative colitis (F54 plus K54).
The division of diseases into mental, somatic, psychosomatic, and somatopsychic is conventional. In any of these pathological states, the entire Organism is affected. Furthermore, at all stages of disease development, numerous changes combine into pathological complexes resembling a peculiar "vicious circle":
Class="center">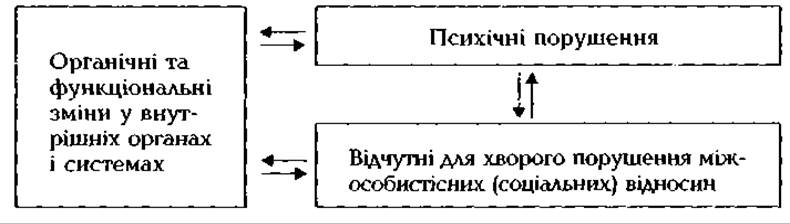
Let's examine this specific "feedback loop." Mental disorders develop under The Influence of both somatogenic factors (such as infectious-allergic, metabolic, vascular, intoxicational, hypoxic, and other pathological processes inherent in a given somatic condition) and psychogenic impacts on the brain, namely the patient's awareness of their life-threatening illness. Furthermore, the deterioration of social status or interpersonal relationships within the family, at work, and elsewhere due to the somatic disease acts as a psychogenic trauma.
In turn, mental disorders disrupt central and peripheral autonomic regulation of internal organs and systems, triggering functional and, subsequently (and quite frequently), organic changes in the somatic sphere—especially within areas of *Locus minoris resistentiae* (organs genetically weakened or compromised by a past pathological process). The secondary adverse impact on internal organs can manifest as patient behavior that is inadequate to their general physical condition, driven by an aberrant personal reaction. For instance, a coronary artery disease patient, firmly convinced they are having a myocardial infarction (personal response), "chains" themselves to bed against the doctor's recommendations. Consequently, hypokinesia impairs myocardial and coronary vessel function. Similar mechanisms explain contractures and other pathological alterations in patients with polyarthritis, those with hereditary predispositions who have undergone ulcer surgery, and others. Occasionally, an inadequate psychological response to illness, such as excessive physical activity, further exacerbates somatic changes.
The restriction of certain social functions—such as the loss of emotionally significant contacts due to illness, the cessation of routine intellectual activities, or the narrowing of social networks—serves as a psychogenic stressor. These factors adversely affect mental activity and, consequently, the condition of internal organs.
Such pathological complexes typically form in individuals with a specific constitutional typology predisposing them to lower resilience against stressors. This primarily concerns people with accentuated, infantile, and psychopathic personality types. An inadequate attitude toward the illness is most commonly observed. For instance, hypochondria may develop, causing the patient to dramatize their condition, groundlessly believing they are severely, incurably, or even terminally ill. Conversely, other patients display an anosognostic attitude toward their condition: disregarding professional advice, they act frivolously, fail to recognize the danger, and neglect medical regimens.
Depressive, histrionic, and other variants of inappropriate response to a somatic Diagnosis are also frequently observed. In such cases, we speak of a disharmonious type of the "internal picture of disease" (L. A. Ouria). Psychological and psychopathological factors complicate somatic pathology. This is a primary reason for its chronic course and "deviation" from typical patterns of development, which complicates medical care and negatively impacts the effectiveness of treatment, Prevention, and rehabilitation.
Based on etiopathogenetic and clinical-dynamic criteria, somatopsychic disorders are classified (O. K. Napryeyenko, 1995) into non-psychotic, psychotic, and defect-organic categories.
Non-psychotic disorders include neurotic, psychopathic, neurosis-like, and psychopath-like disorders (asthenic, astheno-depressive, astheno-hypochondriac, astheno-abulic, astheno-apathetic, anxiety-phobic, obsessive-phobic, depressive, depressive-hypochondriac, hysterical-hypochondriac syndromes, and pseudodementia) that follow a course of: a) reactive responses; b) persistent states; c) pathological personality development.
Psychotic disorders encompass coma, sopor, stupor, asthenic confusion, delirium, oneirism, ammentia, altered states of consciousness, paranoid, depressive, anxiety-, and hallucinatory-paranoid, cenesthetico-hypochondriac, manic-paranoid, catatonic states, symptomatic mania, and Korsakoff's syndrome. Their clinical course is divided into: 1) acute symptomatic; 2) subacute (protracted, intermediate, transitional); 3) chronic (prolonged).
Defect-organic, or encephalopathic, disorders include simple psychoorganic, epileptiform, Korsakoff's, and pseudoparalytic syndromes, as well as nonspecific organic dementia.
Clinical Picture
Cardiovascular System. Coronary artery disease is one of the most prevalent psychosomatic disorders. According to F. Dunbar and several other researchers, it occurs twice as frequently in "coronary personalities" exhibiting Type A behavior patterns. Key traits include ambition, competitiveness, hostility, a constant sense of time urgency, chronic fatigue, and an intense focus on life restrictions and prohibitions. Psychosocial risk factors also encompass socioeconomic hardships and other prolonged stressful situations.
Angina pectoris, arrhythmias, and coronary spasms typically occur in individuals with Type A behavior against a backdrop of chronic anxiety, irritability, anger, aggression, and frustration. Angina is frequently accompanied by atypical substernal pain, dyspnea, and tachycardia, which intensify during spikes in anxiety or panic disorder.
Peripheral vascular spasms in Raynaud's disease are directly linked to substance dependencies such as smoking, as well as prolonged distress.
Somatopsychic disorders in cardiovascular diseases generally arise from two primary causes:
1) cerebral Hypoxia (resulting from decreased Cardiac Output, which leads to impaired cerebral Circulation, alongside combined coronaro-cerebral vascular changes);
2) psychogenic mechanisms (resulting from emotional distress regarding actual or perceived complications of the cardiac condition).
The first scenario presents transient or more persistent neurosis-like and psychopath-like states, as well as states of clouded consciousness. Psychogenias primarily manifest as phobic and anxiety-phobic disorders, and less frequently as depressive, asthenic, and depressive-hypochondriac disturbances.
In cases of myocardial infarction, anxiety and acute psychoorganic syndromes frequently appear in the first few days, while cognitive impairment and depression often emerge during the rehabilitation phase. Patients complain of insomnia, fatigue, poor concentration, and hypochondria. Following heart surgery, alongside psychogenic syndromes—particularly against the backdrop of a deteriorating general condition—patients may exhibit delirious, delirious-ammentive, and delirious-oneiroid clouding of consciousness.
In hypertensive disease and atherosclerotic (combined) coronary and cerebral vascular changes, depending on the stage of the "primary" illness, various mental disorders develop—ranging from neurasthenia-like states to intellectual-mnestic impairments (including nonspecific organic dementia). Furthermore, in these same patients—especially when vascular pathology is combined with other etiological and pathogenic factors (somatic illness, alcoholism, traumatic brain injury sequelae, or neuroinfections)—episodes of impaired consciousness, paranoid and depressive-paranoid states, and epileptiform seizures may be observed.
Da Costa's syndrome ("soldier's heart") was first described during the American Civil War (1871). An unfounded conviction of having a heart disease is accompanied by tachycardia, dyspnea, substernal pain, and profound fatigue. This syndrome is particularly widespread and frequently triggers intense anxiety and panic states.
Respiratory System Disorders. Hyperventilation syndrome has a psychosomatic developmental mechanism: generalized anxiety and panic disorder cause breathing to become rapid and shallow, accompanied by dizziness, tinnitus, headaches, numbness and tingling in the extremities, chest discomfort, fainting, and subsequently, a sensation of suffocation. Coronary insufficiency can lead to fatal outcomes. Bronchial asthma attacks frequently manifest for the first time and recur under the influence of anger, fear, or emotional agitation.
Anxiety and depression in patients with Chronic Bronchitis serve as clear examples of somatic-related psychological distress. In the presence of hypoxemia, cognitive processes may also be impaired.
Gastrointestinal Disorders. Numerous studies confirm the potential psychosomatic etiology of peptic ulcer disease of the stomach, duodenum, and Esophagus. It most commonly affects individuals exposed to chronic stressors. F. Alexander noted that unfulfilled love also acts as a subconscious psychological stimulus directly linked to physiological processes, ultimately leading to ulcer formation. Other theories suggest an infectious origin for the disease as well. Psychopathological symptoms may be driven by hyperactivity of the sympathetic nervous system (dry Mouth, aerophagia, frequent or loose stools), hysterical manifestations, or anxiety-phobic disorders. Abdominal pain, including chronic pain, occasionally has a psychological basis. For instance, psychopathological symptoms accompanied by psychalgia have sometimes led to appendectomies despite a healthy Appendix. Depressed mood, emotional distress, and psychosocial problems frequently precede the onset and recurrence of Crohn's disease, ulcerative colitis, and irritable bowel syndrome.
Disorders of the digestive tract can develop against the backdrop of somatic asthenic and astheno-hypochondriac states of a neurotic register. Obsessive, overvalued, and occasionally paranoid thoughts—predominantly of a Cancer-phobic nature—are less commonly observed. While psychiatric disorders in gastritis are typically limited to neurotic deviations of varying severity, liver diseases (due to intense intoxication and other metabolic disturbances) frequently present persistent neurosis- and psychopath-like states dominated by depressive, hysterical, and hypochondriac features, or combinations thereof. Significant Impairment of the liver's detoxifying function can trigger virtually all forms of altered consciousness, including dysphoria and depressive-paranoid disorders. In hepatolenticular degeneration, due to degenerative changes in both hepatic and cerebral Tissues, psychopathological manifestations are clinically diverse (dysphoria, psychopath-like personality changes, catatono-paranoid states, epileptiform seizures, and intellectual-mnestic decline). Liver cirrhosis is marked by intellectual decline, asthenic, and subsequently apatho-abulic disorders. Patients with dumping syndrome experience hypo- and hyperglycemic autonomic crises against a backdrop of neurotic disturbances. Nearly half of patients who undergo colostomy or ileostomy develop depressive and other psychopathological states, largely driven by psychosocial challenges associated with living with a stoma. Tumors of the digestive organs are frequently accompanied by depression, somnolence, and anhedonia.
Genitourinary system disorders. Psychosomatic disorders observed in urological practice include the so-called irritable bladder (frequent, sometimes painful urination and Urinary Incontinence), Cystalgia (pain in the bladder area and increased tenderness upon Palpation), and dysuria (often combined with "urethral syndrome"). In the absence of any pathomorphological, infectious, or other objective changes, such patients exhibit persistent neurotic depressive-hypochondriacal states and pathocharacterological personality development. The psychogenic nature of such conditions is evidenced by the effectiveness of psychotherapy.
In genitourinary system diseases, the range of clinical manifestations of somatopsychic disorders is wide. Their onset (in cases of acute or chronic renal failure) is primarily driven by disturbances in Water-electrolyte and acid-base Homeostasis, protein or Lipid Metabolism, arterial hypertension, and pathological autoimmune processes, which act as purely somatogenic factors and cause organic changes in brain tissue. As a result, neurosis-like and psychopath-like disorders, as well as psycho-organic syndrome, develop. Such patients may experience severe forms of altered consciousness—delirium, amnesia, oneiroid states, asthenia with clouding of consciousness, deep stupor, and coma. Three stages of neuropsychiatric pathology formation are distinguished. The first is characterized by varying degrees of asthenia symptoms: initially, hypersthenic asthenia (sometimes with hypochondriacal features), followed by hyposthenic asthenia with elements of depression, astheno-abulia, and diencephalic paroxysms. As pathological changes in the Kidneys deepen and their function decompensates, stupor develops, eventually progressing to sopor and coma. Such complications are sometimes observed during hemodialysis sessions as well, triggered by sharp shifts in water-electrolyte metabolism and fluctuations in cerebral blood flow. Due to chronic uremic intoxication, especially when complicated by persistent renal hypertension, the second stage of mental pathology forms, where the aforementioned Functional and Structural disorder signs are compounded by symptoms of structural and organic changes with predominant damage to cerebral vessels in the diencephalic region. At the same time, patients note memory impairment, tinnitus, and frequent, severe headaches. Dizziness and a noticeable worsening of well-being occur during weather changes, as well as in spring and autumn. From these signs of psycho-organic syndrome, the third, encephalopathic stage begins to develop. It is characterized by hyperesthesia, mental and physical exhaustion, dizziness, epileptiform seizures, significant memory decline, concrete thinking, a narrowing of interests, explosiveness, and other manifestations of non-specific organic dementia.
In the absence of significant metabolic disturbances, mental abnormalities may arise through psychogenic mechanisms. For example, initial attacks of urolithiasis accompanied by intense pain can cause emotional distress, and sometimes feelings of anxiety, apprehension, and anticipation of complications and adverse social consequences. Individual reactions remain within the bounds of personal resilience, and their intensity rather quickly subsides to baseline levels. However, in patients with anxious-imaginative premorbid personality traits, neurotic reactions may develop, and when attacks are frequent, persistent astheno-hypochondriacal, astheno-phobic, and depressive-hypochondriacal states may emerge. In some cases, particularly under psychosocial distress, psychopathological conditions transform into a neurotic or psychopathic personality type.
In most cases, Mental disorders in Inflammatory Diseases of the genitourinary organs also form via a psychogenic mechanism. The causes of psychopathological states in this group of patients include, on the one hand, psychotoxigenic/psychotraumatic factors, and on the other hand, certain specific features stemming from the unique personogenic nature of genitourinary diseases. Many patients exhibit an intrapersonal conflict of an intimate nature (distress regarding potential consequences of the illness such as infertility and sexual dysfunction). Thoughts about a venereal disease or the belief that all their troubles stem from an abortion can serve as psychotraumatic factors, even though inflammatory genitourinary diseases most often arise from other causes.
In view of the above, psychosocial factors are of particular importance within the aforementioned pathological complex. First and foremost, this refers to the so-called closed mechanism of psychological trauma, which indicates the acquired Nature of the illness. The NEGATIVE IMPACT OF the illness on the patient's interpersonal relationship with a spouse or sexual partner is also significant.
The dynamics of mental disorders in genitourinary diseases should be divided into two stages. The First stage is characterized by irritability, depressed mood with a tint of anxious agitation, rapid physical fatigue and mental exhaustion, Sleep disturbances, headaches, and coitophobia. Additionally, men may experience sexual dysfunction in the form of premature ejaculation, periodic deterioration of adequate erections while maintaining spontaneous ones, and sometimes decreased libido.
In the second stage, patients complain of depressed mood, generalized weakness, loss of initiative, a tendency toward hypochondriacal ruminations, and fears (including those related to intimate relationships). Sexual disorders may be compounded by a noticeable decrease in libido, persistent deterioration of both adequate and spontaneous erections, and blunted orgasm.
The second stage of mental and sexual disorders occurs predominantly in cases of protracted, frequently recurring inflammatory Diseases of the internal reproductive organs.
In endocrine disorders, mental disturbances arise as a result of impaired neurohumoral regulation affecting metabolic processes, as well as psychotraumatic overloads caused by the realization of the negative social consequences of the disease.
The Clinical presentation of mental disorders in this group of diseases is characterized by certain regularities. The first is that an increase in the function of a particular gland is typically accompanied by an intensification of mental function. For instance, Graves' disease (Basedow's disease) is characterized by hyperesthesia, irritability, accelerated thinking, moderate akathisia, a tendency toward phobias (sometimes accompanied by a fear of death), insomnia, and a decline in cognitive ability and concentration. The disease is accompanied by weight loss, autonomic disorders with a predominance of sympathetic nervous system activity (tachycardia, tremor, sometimes convulsions, etc.), and hyperactive tendon reflexes. In severe thyrotoxicosis, the above-mentioned disorders intensify and are supplemented by manic, hallucinatory-delusional, delirious, and amretic states. In contrast to these symptoms, patients with Myxedema exhibit somnolence, affective dullness, slowed thinking, and occasionally manic-like mental states, paranoia, hallucinations, and bradycardia. Physical and mental performance notably declines, reflexes are diminished, etc.
Hyperparathyroidism is characterized by depression, paranoia, and confusion. Patients with hypoparathyroidism may experience memory impairments, anxiety, depression, and confusion. In Cushing's syndrome, symptoms vary widely—from manic-like psychotic states to depression with suicidal tendencies. Addison's disease is accompanied by somnolence, depression, and delirious states. Frequent manifestations of pheochromocytoma include anxiety, fear, panic, tremor, profuse sweating, and a sense of impending doom.
A second general principle is the dependence of psychopathological manifestations on the stage and severity of the endocrine disease. For example, hypothyroidism can give rise to altered states of consciousness, epileptiform seizures, and catatonic disorders. Patients with congenital, severe underdevelopment of The Thyroid Gland (cretinism) are characterized by intellectual developmental delay reaching the level of idiocy.
Porphyria is marked by anxiety, generalized weakness, and sweating, while acute exacerbations feature depression, agitation, paranoia, and visual hallucinations.
It is characteristic that the clinical picture of mental disorders is dominated by manifestations of hypo- or hypersthenic asthenization, against which acute or chronic psychotic or non-psychotic abnormalities develop. As endocrine gland function deteriorates, asthenic symptoms increase, potentially leading to astheno-abulic and apato-abulic states. The psycho-organic spectrum is frequently disturbed, sometimes progressing to non-specific organic dementia.
Orthopedics and traumatology. Psychosomatic mechanisms of development are observed in Connective Tissue diseases such as systemic lupus erythematosus and rheumatoid Arthritis. The development and exacerbation of these conditions are linked to chronic distress, depression, and anger. Psycho-organic syndromes form during systemic disorders. Anxiety and depression play a significant role in the development of osteoarthritis.
In diseases and INJURIES OF THE musculoskeletal system, the clinical manifestations of mental disorders are largely determined by the degree of motor activity restriction and pain intensity. The following psychopathological phenomena are identified, which contribute to shaping certain personality traits against the Background of a physical defect. Unfounded anxiety about The Fate of loved ones, uncertainty about the future, emotional tension, and fear of pain emerge, alongside a diminished sense of self-worth. Asthenia is driven both by the underlying organic process (infection, metabolic disturbances, etc.) and by psychological reactions to psychological trauma. In hypochondria, the patient is excessively preoccupied with their health, doubting the possibility of recovery, a favorable course of the "primary" illness, or compensation for lost function, all of which take on the character of a psychogenically induced obsessive idea. The conviction that the illness is severe, the hyperbolization of its negative consequences (both for oneself and for loved ones), general malaise, and pain in various PARTS OF THE body may manifest as psychogenic depression. Depression or subdepression is caused by feelings of helplessness, changes in social status, deteriorating relationships at work and home, financial strain, overwork, insomnia, cosmetic defects, etc. Obsessive symptoms (vivid, affectively charged with critical insight, obsessive fears, and less commonly, doubts) are psychogenic in nature. They combine with one another and with asthenia, depression, or subdepression. Thought Disorders primarily involve The Emergence of compensated or decompensated overvalued ideas, which represent a pathologically altered, emotionally charged reaction dominated in consciousness by physical defects, pain, and the social consequences of the disease. Psychalgia (pain of varying localization caused not by objective changes in organs and tissues, but by painful psychological experiences) develops under the influence of a stressful situation. It may combine with genuine physical pain and potentiate it. Therefore, determining the specific weight of psychalgia in the clinical picture is important. It may present as a distinct neurotic disorder syndrome, particularly in those who have experienced intense pain in the past. Sometimes psychalgias emerge as a defensive organismic response to a complex life situation (hypercompensation), while occasionally acting as a manifestation of secondary gain (rent-seeking attitudes). Vegetative-vascular dystonic disorders can result from The impact of infectious-allergic, pathological metabolic, neurohumoral factors, and hypoxia on the central structures of the autonomic nervous system. Sleep disturbances, attention deficits, irritability, and appetite loss stemming from various causes—primarily pain and hypodynamia—play a substantial role in the overall maladaptation of patients.
A distinctive feature of the aforementioned psychopathological manifestations in patients with musculoskeletal disorders compared to the general population is their hypochondriacal fixation on interoceptive sensations,
Under the influence of infection, hypoxia, intoxication, metabolic pathology, and other factors typical of orthopedic conditions, sensations in the osteoarticular-muscular system often transition into interoceptive hyperpathy, caused by a lowered threshold for pain stimuli. The patient's thoughts remain fixed on the affected organ, and sufferers frequently complain of localized pain corresponding to reflex zones in the affected musculoskeletal region. While these sensations are quite polymorphic, the same patient consistently points to their localization and describes them uniformly (stabbing, bursting, burning pain, etc.). Painful experiences are typically affectively charged, but the state of the emotional sphere varies widely, extending even to apathy, which is frequently observed in cases of hypodynamia. The latter is explained by objective changes in bones, muscles, and joints, and/or obsessive-phobic experiences. In such cases, hypochondria can reach delusional proportions accompanied by ideas of reference, self-blame, and a decline in activity and certain vital functions.
For instance, in half of the patients, There is a direct correlation between the stage of the disease (exacerbation or remission) and the manifestation of mental disorders. In a third of patients, so-called psychosomatic balancing is observed, wherein an improvement in somatic status is accompanied by the activation and exacerbation of psychopathological symptoms. In nearly 18% of patients, no such correlational relationship is established; mental abnormalities are "detached" from organic pathology, or the latter is completely unapparent to orthopedic specialists. In these instances, the pain is migratory in nature, accompanied by body schema disturbances and primary disorders of Muscle sensation that do not correspond to topographical zones of spinal and peripheral innervation. In other words, this represents a primary mental pathology accompanied by coenesthesias, mimicking the symptoms of a non-existent condition in the given patient.
Typical clinical manifestations of mental disorders specific to particular localizations of orthopedic pathology have not generally been identified. However, there is a moderate increase in the frequency of depressive reactions associated with functional impairment of the lower extremities, which is likely attributable to a predisposition toward hypodynamia. Patients with the consequences of spinal Column injuries also predominantly exhibit depressive symptoms, frequently revealing suicidal tendencies and, less commonly, apathy.
Oncological diseases. In cases of extra-cerebral tumor localization at the onset of the disease (prior to the detection of a mass-occupying process), mental disturbances present as somatogenic asthenia. When general somatic status is poor, this combines with anxious tension and affective lability. Anosognosic coping—where the patient attempts to "escape from the illness"—is quite common. The very fact of tumor detection is typically a powerful psychotraumatogenic moment and may provoke anger, disbelief, anxiety, and despair. A severe depressive reaction, sometimes with suicidal tendencies, frequently develops. Most often, the psychiatric diagnosis is formulated as an adjustment disorder. As cancer intoxication and other somatic disturbances progress, signs of asthenia gradually intensify, accompanied by a sense of deep sadness. Against this backdrop, an anxious-phobic state periodically emerges. The Need for radiation and Chemotherapy can provoke anxiety, fear, and other emotional disturbances, with psychogenically induced nausea, generalized weakness, and other somatic sensations appearing even before treatment begins. Patients with cachexia frequently experience delirious disorders, with illusory, hallucinatory, and delusional experiences often directed toward medical personnel, which explains the patient's suspiciousness and inadequate behavior. Psychological abnormalities are usually transient, but depressive-paranoid states, Cotard's delusion, and Korsakoff's syndrome occasionally take on a protracted course.
In the pre-terminal stage of the disease, astheno-abulic and subsequently apato-abulic states are observed, reaching the degree of apathetic stupor, which indicates an extremely severe general condition. Harbingers of agony in such patients are often muttering delirium or amentia transitioning into coma. Occasionally, death occurs following prolonged euphoria.
Nervous system diseases. Among psychosomatic disorders observed in neurology clinics, psychogenic hyperesthesia is the most common. It manifests as skin hypersensitivity and an intensification of visual, auditory, gustatory, and olfactory sensations, reaching what V. D. Topolyansky and M. V. Strukovsky (1986) termed "painful hyperpathy." Psychogenic reduction of tactile, and particularly pain and Temperature sensitivity of the skin and mucous membranes, up to complete anesthesia (most common in hysterical disorders), is also observed. Hyperesthesia is frequently combined with "psychogenic neuralgia and myalgia," which when localized in the left intercostal spaces or the breast area, often lead to hypochondriacal fixation—namely, cardiophobia and cancerophobia. The non-organic nature of these sensations is indicated by their "migratory" character, and they are predominantly manifestations of masked somatized depression. Since this type of depression is often endogenous, terms like "psychogenic neuralgia" and "myalgia" are conventional. Affective Disorders underlie a whole range of psychogenic dyskinesias: writer's cramp (difficult, distorted writing), musician's cramp (in pianists, violinists, etc.), milker's cramp, and calf muscle spasms in ballerinas, among others.
Somatopsychic disorders are observed in the clinical picture of many neurological lesions, largely explained by the psychosocial problems faced by patients (disabling conditions, restricted mobility, social isolation, etc.). For instance, children with muscular dystrophy exhibit sadness, depression, and irritability. In multiple sclerosis, patients become uninhibited, anxious, and euphoric due to various causes, and manic states may develop.
Obstetrics and gynecology. Psychogenic mental disorders are observed predominantly During the first and last trimesters of pregnancy, driven primarily by childbirth fears and anxiety over fetal development. Sometimes negative experiences stem from unwanted pregnancy (in single women), difficult marital relations, financial hardship, etc. Psychosomatic mechanisms are observed in severe hyperemesis gravidarum (excessive vomiting in pregnancy). Mental disorders, and depression above all, can become the primary cause of habitual miscarriages. The so-called pseudocyesis (phantom pregnancy) is psychogenic in nature, occurring when a woman is convinced she is pregnant without physiological grounds; this state is sometimes accompanied by Amenorrhea and other early pregnancy signs. Various neurotic disorders may arise in women following medical abortions. L. Bogdan (1983) described the couvade syndrome (from French couvade — hatching of eggs): the pregnant woman's partner reported experiencing certain pregnancy symptoms, including morning nausea, general weakness, and toothaches. In the first days postpartum, many women (most often primiparas, those prone to depressive reactions, or those with "premenstrual tension syndrome") experience excessive emotional lability (ranging from euphoria to profound sadness), depressed mood, emotional tension, and irritability. Approximately two weeks after delivery, postpartum psychosis may develop in new mothers, differing little in its clinical course from that in the general population. This occurs mainly in women with a history of past psychiatric disorders or a burdened family psychiatric history. Affective (predominantly manic) psychosis is diagnosed in 80% of cases, followed in prevalence by schizophrenic psychosis and, thirdly, psycho-organic psychosis. When diagnosing such disorders, it is crucial to ascertain the mother's intentions toward the infant, as instances of aggression toward children can occur. Suicidal intents among postpartum women are also dangerous.
Premenstrual syndrome is a complex of psychopathologic (irritability, anxiety, depression) and somatic (breast tenderness, discomfort) symptoms that appear a few days before menstruation and disappear after its onset. During menopause, depressive and anxiety states become more frequent, accompanied by hot flashes, hyperhidrosis, and vaginal dryness.
Blood disorders. In leukemia, lymphoma, and hemophilia, the most common psychopathologic symptoms are anxiety and psychogenic vomiting.
Burns. Psychological and psychosocial factors play a significant role in the occurrence of burns. For instance, burns frequently occur in hyperactive and intellectually disabled children, as well as those from dysfunctional families. Among adults, burns are most commonly seen in individuals with cognitive impairments, alcohol or substance abuse, etc. Somatopsychic disorders, manifesting as asthenia, depression, and—in cases of intoxication—psychotic symptoms, are observed in over a third of patients with burn disease, particularly when disfigured appearance is involved.
Skin diseases. Most researchers classify neurodermatitis as a classic psychosomatic disorder, because the onset or exacerbation of eczematous changes in this condition is directly linked to emotional distress (such as the death of a loved one), suppressed anger, or sexual problems. Skin alterations occur against the backdrop of stress, chronic anxiety, and depression (as seen in urticaria and angioedema). The idiopathic type is usually unrelated to specific allergens or any physical pathogens. Some researchers also suggest including lichen planus, vitiligo, psoriasis, atopic dermatitis, alopecia areata, and pruritus in this group of disorders.
Sensory disorders. Individuals with prelingual deafness are more likely to experience behavioral disorders and social isolation rather than psychiatric disorders. If deafness progresses rapidly in a person who has already acquired speech, depression may develop. A link between deafness and persecutory delusions has also been identified. Blindness likewise serves as a trigger for depression and psychosocial maladjustment when Vision is lost later in life rather than during childhood.
Diagnosis
When diagnosing a psychosomatic disorder, it is necessary to identify: a somatic disorder or pathophysiological process (e.g., enuresis); the primary psychological factor directly associated with the onset or exacerbation of the somatic disorder; and the third component of the pathological complex operating as a "vicious circle" (pathogenic microsocial factors).
Differential diagnosis should be performed to rule out the following conditions: somatized psychotic disorders (characterized by multiple, sometimes shifting Complaints of organic changes despite a lack of objective confirmation); hypochondriasis (excessive anxiety regarding somatic health, "preoccupation" with a non-existent or exaggerated illness); somatoform disorder (unpleasant physical sensations described with hysterical demonstrativity, even though somatic examinations reveal no pathology); dysmorphophobia (a pathological belief in a non-existent physical defect that is resistant to logical correction); clinical manifestations of major psychiatric disorders (such as asthenia and general weakness in endogenous depression); and somatic disorders associated with substance use (for instance, smoker's cough). Thus, the primary differential diagnostic criterion for a psychosomatic disorder is the presence of a verified organic or pathophysiological disease process.
If a patient seeks psychiatric consultation again, they should undergo a thorough re-examination to avoid clinical misdiagnosis.
Treatment
The therapeutic management includes: psychological and psychotherapeutic work with the patient; psychological and psychotherapeutic support for their family and immediate social circle; and the administration of psychotropic medications (along with other psychocorrective Methods combined with treatments prescribed by primary care physicians or specialists).
Tranquilizers (such as Rudotel, Radedorm, Tranxene, Eglonyl, Sibazon, Relanium, Tazepam) and antidepressants (such as Amitriptyline, Cipramil, Prozac, Zoloft, Azafen, etc.) are predominantly used. For psychotic disorders, Haloperidol, Trifluoperazine, Clopixol, Fluanxol, Zyprexa, Risperdal, Solian, etc., are also employed. These are prescribed alongside correctors (Parkopan, Cyclodol) and general tonics (multivitamins, Magne B6, Berocca, etc.). In addition to achieving a psychotropic effect, the treatment aims to eliminate pain and normalize behavioral responses altered by pain and somatic dysfunction.
At the same time, one must account for the increased sensitivity of somatically ill patients to psychotropic medications, and occasionally their paradoxical response to them. Therefore, these drugs are initially prescribed in small doses, which are then increased depending on individual tolerance and somatic status. Particular caution must be exercised in the presence of parenchymal organ diseases. Psychotherapy should remain the cornerstone of treatment.
Prophylaxis
The prevention of psychosomatic and somatopsychic disorders is traditionally divided into primary, secondary, and tertiary. Primary prevention consists of the early detection of factors contributing to the onset of psychosomatic disorders, as well as the effective treatment of somatic diseases and the Structure/175.html">Implementation of measures to prevent somatopsychic disorders. Secondary prevention involves therapeutic and social measures aimed at preventing relapses of both the somatic illness and its associated psychiatric complications. To achieve this, supportive courses of psychocorrection are conducted in outpatient or inpatient settings in parallel with somatic treatments. Tertiary prevention is prescribed to prevent Various Forms of pathological personality development or mental disability. This involves analyzing The structure of the disease-altered personality, pathognomonic clinical manifestations, and psychotraumatic circumstances. Subsequently, measures are taken to eliminate or neutralize these situations (stressors) and to reorient the individual toward positive social aspects. In cases of organic cerebral pathology, appropriate etiological and pathogenetic treatment is administered.
Prognosis
The prognosis is determined comprehensively, based on criteria established for specific groups of somatic diseases while taking into account the Features of the psychiatric pathology.
Expert Evaluation
Military, occupational, and forensic-psychiatric expert evaluations are conducted following the same principles as prognosis determination.
1. Definition and classification of psychosomatic disorders.
2. Etiology and pathogenesis of psychosomatic disorders.
3. Clinical manifestations of psychosinoses.
4. Definition and classification of somatopsychic disorders.
5. Pathogenetic mechanisms of somatopsychic disorders.
6. Clinical manifestations of mental disorders in cardiovascular and respiratory system diseases.
7. Mental disorders in diseases of the digestive system.
8. Psychopathology in genitourinary system diseases.
9. Mental disorders in endocrinopathies.
10. Psychopathology in orthopedics and traumatology.
11. Main psychopathological manifestations in neurology, dermatology, oncology, hematology, obstetrics and gynecology, and in sensory disorders.
12. Principles of Diagnosis and treatment of psychosomatic and somatopsychic disorders.
Last update: 10/08/2026
Editorial and Educational Adaptation: This material has been compiled based on the primary/original source text. The project team performed an editorial review, corrected technical inaccuracies, structured sections, and adapted the content for an educational format.
What was processed:
- elimination of formatting defects (OCR errors, structural breaks, corrupted characters);
- editorial organization of content;
- standardization of terminology in accordance with academic sources;
- verification of factual statements against the original source text.
All mentions of the author, publication year, and origin of the primary text have been preserved in accordance with the source.