MEDICAL BIOLOGY, ANATOMY, PHYSIOLOGY AND HUMAN PATHOLOGY - Y.I. Fedoniuk 2010
ANATOMY, PHYSIOLOGY, PATHOLOGY
CHAPTER 7. THE NUTRITIONAL PROCESS AND ITS PATHOLOGY
PATHOLOGY OF THE DIGESTIVE SYSTEM
GASTRIC PATHOLOGY
3. PEPTIC ULCER DISEASE
Peptic ulcer disease is a chronic, cyclically recurring condition with a tendency to progress, characterized by The formation of a defect in the mucous membrane of The Stomach or duodenum resulting from diminished mucosal defense or increased aggressiveness of gastric contents.
Peptic ulcer disease predominantly affects individuals of peak working and creative age, frequently leading to temporary and sometimes permanent disability.
When determining the Etiology of this disease, the following factors should be taken into account.
1. Prolonged and frequent neuro-emotional stress.
2. Genetic predisposition, including a constitutionally determined persistent elevation of gastric juice acidity (Blood group A (I) occurs significantly more often in peptic ulcer patients compared to the general population).
3. The presence of Chronic gastritis, duodenitis, and hypersthenic-type functional Disorders of the stomach and duodenum (pre-ulcer state).
4. Irregular eating habits.
5. Smoking.
6. Consumption of strong alcoholic beverages and certain medications (acetylsalicylic acid, butadion, indomethacin, etc.).
Morphologically, a distinction is made between simple (acute) and callous (chronic) peptic ulcers located in the stomach or duodenum. A simple ulcer features soft edges without marked scarring; a callous ulcer is characterized by severe connective-tissue thickening of the edges and inflammatory-scarring changes around it.
Ulcers are most commonly located in the duodenal bulb. Gastric ulcers are predominantly found along the lesser curvature, near the angle of the stomach and the pyloric region, and less frequently in the cardiac region and the greater curvature. Rarely, an ulcer is located beyond the duodenal bulb.
An ulcer differs from an erosion in that it affects not only the mucosa but also the submucosa, sometimes penetrating deeper layers of the gastric or duodenal wall (Fig. 7.28). A deep ulcer that penetrates through the wall layers directly into an adjacent organ (Liver, Pancreas, omentum, etc.) is termed a penetrating ulcer.
Class="center">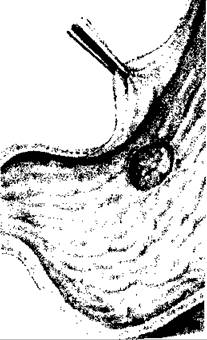
Fig. 7.28. Chronic Gastric Ulcer
If, as necrosis progresses, the ulcer ruptures directly into the Abdominal cavity, it is referred to as a perforated ulcer.
The Base of the ulcer is typically filled with necrotic or granulation tissue (during the healing phase); its surface is covered with a film composed of necrotic tissue, fibrin, leukocytes, and erythrocytes.
Healing of an ulcer results in scar formation. In chronic cases and with large ulcers, the resulting scars deform the stomach and the duodenal bulb. Rough scarring of the pyloric region of the stomach is accompanied by The Development of pyloric stenosis. If in the area
of the ulcer base There is a major blood vessel, erosion of its wall due to progressive necrosis leads to a severe complication: profuse Hemorrhage.
Last update: 08/08/2026
Editorial and Educational Adaptation: This material has been compiled based on the primary/original source text. The project team performed an editorial review, corrected technical inaccuracies, structured sections, and adapted the content for an educational format.
What was processed:
- elimination of formatting defects (OCR errors, structural breaks, corrupted characters);
- editorial organization of content;
- standardization of terminology in accordance with academic sources;
- verification of factual statements against the original source text.
All mentions of the author, publication year, and origin of the primary text have been preserved in accordance with the source.