BIOTECHNOLOGY - V. H. Herasymenko - 2006
Part II. Special Biotechnologies
CHAPTER 8. THE USE OF IMMOBILIZED PREPARATIONS FOR THERAPEUTIC PURPOSES
8.2. METHODS OF IMMOBILIZATION AND APPLICATION OF PREPARATIONS
The immobilization of therapeutic Enzymes and other protein preparations can be carried out using various Methods of covalent and non-covalent fixation of enzymes onto insoluble and soluble carriers of diverse origins. The choice of method depends on the intended purpose of the preparation and its route of administration.
There are two fundamentally different approaches to the production and application of immobilized therapeutic enzymes: 1) administration into the Organism; 2) utilization in reactors via an extra-organism shunt (artificial Kidney) or implantation of a Reactor with an immobilized enzyme functioning as a Blood vessel prosthesis.
The first approach encompasses variants that depend on the pathological conditions of the organism. In various systemic disorders, when the presence of a therapeutic enzyme is required across different Organs and Tissues, it is advisable to use a Water-soluble preparation immobilized by one method or another, which exhibits enhanced stability and prolonged clearance from the body. These include various enzyme-containing "artificial Cells" such as microcapsules, Liposomes, and erythrocyte "ghosts".
On the other hand, for the Treatment of localized lesions, where the enzyme's presence is required solely at the site of pathology, it is appropriate to create biocompatible enzyme-containing polymer constructs (either biodegradable or simply temporarily implanted) that can be localized at a specific site and remain there for a certain period, continuously releasing the therapeutic enzyme into the surrounding environment.
Immobilized enzyme preparations for local application can be produced using either insoluble polymers or biodegradable carriers. In the first case, the carrier is mechanically removed from the lesion site once the enzyme action is complete, whereas In the second case, it undergoes natural degradation within the tissues.
Preparations of thrombolytic enzymes with a predetermined biodegradation rate—namely fibrinolysin, streptokinase, and urokinase—have been developed using cross-linked sephadex dextran microgranules. They can establish a local depot for the treatment of thrombosis.
The second approach to the production and application of immobilized enzymes involves their use in various extracorporeal devices for the perfusion-based purification of biological fluids.
Extracorporeal perfusion using enzymes is widely employed for the removal of toxins from the body. The carriers used are spherical particles made of polymers, Glass, ceramics, or silicates. The requirements for these carriers are as follows: they must exhibit minimal nonspecific sorption, must not cause deformation of blood cellular elements, and should be cost-effective, given that hemodialysis and detoxification columns are single-use devices.
A specific case of this approach is the creation of enzyme reactors used as thromboresistant blood vessel prostheses. This category also includes dressings, which typically contain Proteolytic Enzymes used for cleansing purulent wounds.
When treating systemic disorders, soluble preparations of immobilized Enzymes can be administered via traditional intravenous injection. However, intraperitoneal administration is preferable, as catalytic activity is maintained there for up to 8 months. For instance, dextran-modified carboxypeptidase G and arginase administered intraperitoneally to mice with grafted mastocytoma are capable of generating a higher and more sustained active concentration in the bloodstream than native enzymes. Immobilization on soluble polymeric carriers yields more stable, active, and safe therapeutic preparations. This method successfully allows the immobilization of other protein-based agents—various physiologically active Polypeptides such as the pancreatic Trypsin inhibitor and, crucially, the hormone Insulin.
A promising method of immobilization and application of modified enzyme forms for therapeutic purposes involves the creation of various types of "artificial cells".
Medicinal preparations in which the protein-to-polymer mass ratio is extremely high, reaching hundreds of thousands and above, can be produced using the so-called "artificial Cell" method, as well as liposomes. These preparations function as a sort of microsphere enclosed by a more or less rigid and permeable membrane, serving various purposes.
The first type of "artificial cells" consists of microcapsules, which were developed by T. M. Chang in 1965. Microencapsulated enzyme preparations are tiny reactors ranging from 103 to 5104 nm in diameter, featuring a thin polymer membrane (200-400 nm) that is permeable to low-molecular-weight compounds, namely low-molecular-weight substrates and their conversion products. The enzyme contained within the membrane is securely retained, avoids direct contact with biological fluids and body tissues, resists degradation by proteinases, remains uninhibited, and does not trigger an Immune Response. These microcapsules can encapsulate relatively high concentrations of the enzyme—levels unattainable in the bloodstream when using native enzymes—as well as multiple different enzymes simultaneously.
The primary advantage of microcapsules is The ability to implant them directly into a target site, such as in the immediate vicinity of a tumor. The encapsulated enzyme can be pre-stabilized, or co-encapsulated with other high-molecular-weight compounds that facilitate its stabilization.
Microcapsules can also contain microscopic tissue fragments. For example, experimental data exist on establishing an insulin depot within the body by implanting microcapsules containing the islets of Langerhans, which synthesize insulin in the Pancreas (Berezin et al., 1987).
Multi-enzyme systems and their Cofactors, modified to increase their molecular weight and ensure retention within the microsphere, can be incorporated into the interior of microcapsules.
The polymer wall of microcapsules is typically manufactured from durable synthetic polymers (such as polyamides and polyurethanes) or natural polymers (such as polylactic acid). Polylactic acid biodegrades at a sufficient rate, thereby eliminating Structure/149.html">The problem of microcapsule shell disposal in the body, which makes such enzyme preparations highly promising. Nevertheless, microcapsules made from synthetic polymers are exceptionally effective for extracorporeal Applications, such as dialysis columns in artificial kidney machines. This approach significantly reduces the volume of the preparation and, consequently, the required amount of expensive solutions. For instance, a microencapsulated "artificial kidney" requires a Column with a volume of only 30 ml, operating nearly 100 times faster than a conventional apparatus.
Urease along with a carrier (an ion-exchange resin or activated carbon) is placed inside a single microcapsule. Ammonia produced during urea decomposition is adsorbed within the microcapsule:
Class="center">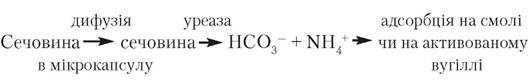
Enzyme reactors based on microcapsules are likely to be utilized for the degradation of non-dialyzable Materials.
In some cases, microcapsules are manufactured using high-molecular-weight compounds that remain soluble under certain conditions while maintaining high membrane integrity under others. An example of this behavior is Cellulose acetate phthalate, whose microcapsules remain intact in gastric juice and dissolve in the intestine, thereby releasing their contents.
Magnetic particles can be incorporated into microcapsules. In this case, an external magnetic field is applied to hold the drug near the target organ (the affected organ).
The first successful experiments involving The Use of microencapsulated enzymes in animals were carried out using urease to lower blood urea, catalase for treating animals with catalase deficiency, and asparaginase to inhibit the growth of asparagine-dependent tumors (Larionova N.I., Torchilin V.P., 1982).
Following microencapsulation, the next method for creating artificial cells is the entrapment of enzymes into liposomes—artificial phospholipid vesicles, also referred to as carrier containers.
Liposomes are bilayer spherical structures ranging from 20 to 103 nm in diameter, typically produced by applying mechanical stress to phospholipid dispersions (Larionova N.I., Torchilin V.P., 1982). Liposomes are entirely biocompatible, do not provoke immunological reactions, and their constituent Phospholipids can be reused for cell membrane synthesis upon degradation. Unlike microcapsules, liposomes are capable of delivering encapsulated drugs directly to the cells they interact with, facilitating the delivery of missing enzymes to Lysosomes. However, within just 15–30 minutes of administration, 50–80% of liposomes are taken up by Cells of the reticuloendothelial system, primarily in The Liver and Spleen. Consequently, the targeted delivery of liposome-entrapped enzymes to specific tissues remains a challenge. Various concepts are being explored to enable liposomes to deliver enzymes precisely to their destination, i.e., the affected organ. To achieve this, it is proposed to incorporate Antibodies onto the liposomal surface that target antigenic structures present On the surface of the destination cells for which the enzyme is intended.
Among the numerous enzymes already incorporated into liposomes, asparaginase—used in the treatment of certain forms of leukemia—is of particular interest. It has been established that some leukemic cells are incapable of synthesizing the amide asparagine and, consequently, cannot proliferate without exogenous asparagine. The intravenous administration of asparaginase immobilized via entrapment in liposomes or polylactic acid capsules reduces the blood concentration of this amide to a minimum level, leading to the death of leukemic cells due to asparagine starvation.
Given that the cells of the reticuloendothelial system, particularly in the liver, serve as a natural target for liposomes, liposome-encapsulated enzymes can prove highly effective in treating various hepatic enzyme deficiencies.
Blood cell ghosts, specifically Erythrocyte membranes, can also serve as containers for enzyme entrapment. These are obtained through the partial hemolysis of erythrocytes, followed by loading the enzyme and subsequently restoring membrane integrity. This method has been successfully used to produce erythrocyte ghosts loaded with β-glucosidase, β-galactosidase, β-glucuronidase, and asparaginase.
In addition to erythrocytes, other cell ghosts are also utilized. For instance, pharmaceutical preparations incorporated into macrophage membranes have been developed (Berezin I.V. et al., 1987). Macrophages tend to accumulate at sites of inflammation, and thus can transport both low- and high-molecular-weight drugs directly to these foci. An advantage of cell ghosts as carriers is their complete compatibility with the human or animal organism, since these carriers are prepared from cells isolated directly from the patient.
Micelles—structures smaller in diameter than liposomes—are also of considerable interest. They hold great promise as enzyme carriers for the formulation of complex ointment compositions in which enzymes are otherwise unstable.
Last update: 11/08/2026
Editorial and Educational Adaptation: This material has been compiled based on the primary/original source text. The project team performed an editorial review, corrected technical inaccuracies, structured sections, and adapted the content for an educational format.
What was processed:
- elimination of formatting defects (OCR errors, structural breaks, corrupted characters);
- editorial organization of content;
- standardization of terminology in accordance with academic sources;
- verification of factual statements against the original source text.
All mentions of the author, publication year, and origin of the primary text have been preserved in accordance with the source.