Review of Medical Physiology - William F. Ganong 2002
The Endocrine System, Metabolism, and Reproduction
Endocrine Functions of the Pancreas and the Regulation of Carbohydrate Metabolism
Hypoglycemia and Diabetes Mellitus in Humans
Hypoglycemia
Insulin reactions are common in type 1 diabetes, whereas rare hypoglycemic episodes are a sign of good glycemic control in most diabetic patients. Physical Exercise increases both Skeletal Muscle glucose uptake and the absorption of administered insulin (see above). Insulin-treated diabetics must learn to anticipate this effect by adjusting their food intake or insulin dose when exercising.
Symptomatic hypoglycemia also occurs in non-diabetic individuals. A review of some of the most critical cases highlights the changes that occur in Blood glucose. Chronic mild hypoglycemia causes slurred and incoherent speech, a condition that can easily be mistaken for intoxication. Mental disturbances and seizures may also occur without coma. When insulinoma, a rare insulin-secreting tumor of the Pancreas, chronically elevates insulin secretion, symptoms are most prominent in the morning. This happens because overnight fasting depletes hepatic Glycogen stores. However, symptoms can appear at any time, sometimes leading to misdiagnosis. Some insulinoma cases have been mistakenly diagnosed as Epilepsy or psychosis. Hypoglycemia also occurs in patients with large non-islet Cell malignancies, where it is partly the result of excessive IGF-II secretion.
As noted above, autonomic symptoms such as tremor, sweating, anxiety, and hunger tend to occur at higher plasma glucose levels than cognitive symptoms, serving as a warning sign to ingest sugars. However, in some individuals, these warning signs do not precede cerebral symptoms, making asymptomatic hypoglycemia potentially dangerous. This condition is most common in patients with insulinomas and in diabetics undergoing intensive insulin therapy. Consequently, recurrent bouts of hypoglycemia eventually lead to hypoglycemia unawareness. If blood glucose is raised again for a time, the warning signs reappear at a higher plasma glucose level than cognitive impairment and coma. The exact reasons why prolonged hypoglycemia causes the loss of warning signs remain fully understood.
In Liver disease, the glucose tolerance curve takes on a diabetic profile, yet fasting plasma glucose levels are low (Fig. 19-20). In functional hypoglycemia, the rise in plasma glucose following a test dose is normal, but the subsequent "overshoot" drops below hypoglycemic levels, triggering symptoms 3 to 4 hours after a meal. This pattern is occasionally observed in individuals who later develop diabetes. Patients with this syndrome must be distinguished from the much larger group of patients with similar symptoms due to psychiatric or other problems, who do not exhibit hypoglycemia on blood tests during a symptomatic episode. It has been hypothesized that the fluctuation in plasma glucose results from insulin secretion stimulated by impulses in the right Vagus nerve, but cholinergic blocking agents do not adequately correct this anomaly.
Class="center">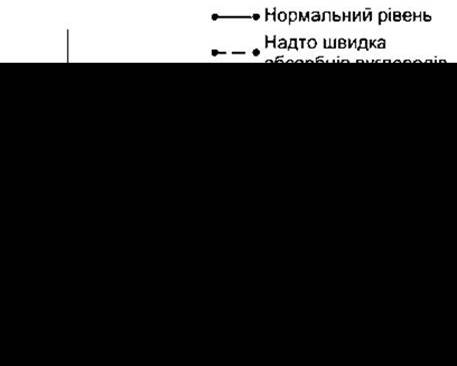
Fig. 19-20. Typical oral glucose tolerance curves in liver disease and in conditions causing excessively rapid intestinal Glucose Absorption. The horizontal line represents the approximate plasma glucose level at which hypoglycemic symptoms may appear.
In some patients with thyrotoxicosis, as well as in those following gastrectomy and other surgeries that accelerate gastric emptying, glucose absorption is abnormally rapid. Plasma glucose rises to a high early peak and then rapidly falls to hypoglycemic levels because the hyperglycemic surge provokes an abnormally large increase in insulin secretion. Characteristic symptoms manifest 2 hours postprandially.
Infants born to diabetic mothers often have high birth weight and organomegaly (macrosomia). This condition is caused by excess circulating fetal insulin, which in turn is partly driven by stimulation of the fetal pancreas by glucose and Amino Acids from the maternal Circulation. Free insulin in maternal blood is degraded by placental proteases, but antibody-bound insulin is protected and thus reaches the fetus. Therefore, fetal macrosomia occurs in women who produce Antibodies to foreign animal insulins and continue to use animal insulin during Pregnancy.
Neonates with GLUT 1 deficiency have impaired glucose Transport Across the blood-Brain barrier. They present with low CEREBROSPINAL FLUID glucose despite normal plasma glucose levels, leading to seizures and developmental delay.
Diabetes mellitus is widespread in humans and also occurs in animals. It is estimated that 5-7% of the United States population is affected by this disease. Diabetes is sometimes complicated by acidosis and coma, and long-standing diabetes leads to additional complications, including microvascular, macrovascular, and neurological disorders. Microvascular lesions include proliferative retinal scarring (diabetic retinopathy) and renal disease (diabetic nephropathy). Macrovascular lesions are caused by accelerated atherosclerosis secondary to elevated plasma LDL levels (see above), leading to an increased incidence of strokes and myocardial infarctions. Neurological pathology (diabetic neuropathy) affects both the Autonomic Nervous system and peripheral nerves. Neuropathy, combined with atherosclerotic circulatory impairment and reduced resistance to infection in severe cases, leads to chronic ulcers and gangrene, particularly in the lower extremities. Retinopathy arises from excessive blood vessel growth, a neovascularization process promoted by Growth Hormone.
The ultimate cause of capillary and neurological complications is chronic hyperglycemia. Strict glycemic control reduces the incidence of these disorders. Intracellular hyperglycemia activates the enzyme aldose reductase, which increases sorbitol production within Cells, leading to a decrease in Na+-K+-ATPase activity. In addition, intracellular glucose can be converted into so-called Amadori products, resulting in advanced glycosylation end products (AGEs) with cross-linking of matrix Proteins. This process damages Blood Vessels; AGEs also impair the leukocyte response to infection.
Types of Diabetes
Clinical diabetes is invariably caused by a deficiency of insulin action at THE TISSUE LEVEL, though this deficit is sometimes relative. One common form, type 1 or insulin-dependent diabetes mellitus (IDDM), results from insulin deficiency caused by autoimmune destruction of pancreatic B-cells, while A-, D-, and F-cells remain unaffected. Another common form, type 2 or non-insulin-dependent diabetes mellitus (NIDDM), is characterized by insulin resistance and impaired insulin secretion. It remains unclear which of these occurs first, but one can envision a scenario where insulin resistance elevates plasma glucose, stimulating insulin secretion until B-cell reserves are exhausted. In this situation, plasma insulin levels are more often elevated than depressed, though not as high as would be expected for the same plasma glucose level under normal conditions.
An international committee recommended the terms type 1 and type 2 (replacing IDDM and NIDDM) for the two common forms of diabetes. Each terminology has advantages; specifically, the terms IDDM and NIDDM convey pathophysiological information. However, the terms type 1 and type 2 are used in this book to align with current international nomenclature.
Diabetes can also result from other diseases or conditions, such as Chronic Pancreatitis, total pancreatectomy, Cushing's syndrome (see Chapter 20), and acromegaly (see Chapter 22). These account for about 5% of all cases and are sometimes classified as secondary diabetes.
Type 1 diabetes typically manifests before the age of forty, which is why it is often referred to as juvenile-onset diabetes. Patients with this condition are not obese and frequently experience ketonemia and acidosis. Type 1 diabetes accounts for about 10% of all diabetic cases. It is a strictly autoimmune disorder characterized by various anti-B-cell antibodies that destroy B-cells. There is a strong genetic predisposition to the disease: if one identical twin develops it, the other has roughly a one-in-three chance of also developing it, yielding a concordance rate of about 33%. The primary genetic abnormality is located within the Major Histocompatibility Complex on chromosome 5, predisposing individuals with specific histocompatibility antigen profiles to the disease (see Chapter 27). Other genes are also involved in these processes.
Some of the antibodies are directed against glutamate decarboxylase (see Chapter 4). Although present in B-cells, this enzyme does not perform the vital Functions there that it does in the brain. In mice, preventing the expression of glutamate decarboxylase in B-cells does not lead to their autoimmune destruction. Immunosuppressive therapy with agents such as cyclosporine ameliorates type 1 diabetes in humans if administered early in the disease process before all B-cells are lost.
Type 2 diabetes is the most common form. It typically develops after the age of 40 and is not dependent on a loss of insulin secretory capacity. The onset of the disease is insidious, and ketonemia is rare. B-cell Morphology is normal, and B-cell insulin stores are not depleted. Most patients with this form of diabetes are obese, and their glucose tolerance improves with weight loss. Typically, there is an exaggerated, prolonged insulin response to glucose that develops slowly and is secondary to an inadequate early B-cell response. This response fails to suppress hepatic glucose output to normal levels, and the resulting hyperglycemia drives the late insulin response. Patients with type 2 diabetes have a normal number of GLUT 4 transporters in their insulin-sensitive cells, but these cells fail to translocate sufficient transporters to The Cell membrane in response to Insulin Receptor activation. A prominent feature of the disease is strong genetic heritability. For example, the concordance rate for type 2 diabetes in identical twins is much higher than for type 1, reaching nearly 100% in some populations.
A subset of patients with type 2 diabetes harbor Genetic Defects in glucokinase (approx. 1% of cases), the insulin molecule itself (approx. 0.5%), the insulin receptor (approx. 1%), GLUT 4 (approx. 1%), or IRS-1 (approx. 15% of all cases). In maturity-onset diabetes of the young (MODY), which accounts for 1% of type 2 diabetes cases, three loss-of-function Mutations have been described. One occurs in the glucokinase Gene (see Fig. 19-14), the enzyme responsible for Glucose METABOLISM in B-cells (MODY2); another in the gene encoding the Transcription factor HNF-1a (MODY3); and a third in the gene for HNF-4a, a regulator of HNF-1a expression (MODY1). Nevertheless, the underlying cause of type 2 diabetes remains unknown in the majority of cases.
Last update: 10/08/2026
Editorial and Educational Adaptation: This material has been compiled based on the primary/original source text. The project team performed an editorial review, corrected technical inaccuracies, structured sections, and adapted the content for an educational format.
What was processed:
- elimination of formatting defects (OCR errors, structural breaks, corrupted characters);
- editorial organization of content;
- standardization of terminology in accordance with academic sources;
- verification of factual statements against the original source text.
All mentions of the author, publication year, and origin of the primary text have been preserved in accordance with the source.